Who we are.

Join the fight against pancreatic cancer! The 2015 Pancreatic Cancer Research Walk is Sunday, November 1st at Sloan's Lake Park, Denver, CO.

All the money raised goes directly to pancreatic cancer research thanks to the Lustgarten Foundation!

Sunday, October 09, 2011

Volunteer Opportunities in Denver!


Are you or someone in your family struggling with pancreatic cancer?  

Do you want to get involved and help fight this awful disease?  

Join the team of Coloradans running the Lustgarten Pancreatic Cancer Walk. It's an annual event started by the Phillips Family that's held at Sloan's Lake each November.  

While there is a dedicated team, we can always use more help!!  Not only would you be supporting a great cause, but you'll also have the opportunity to others whose lives have been touched by pancreatic cancer.  We're one community fighting for a cure.

What to volunteer?  Email us at: rphill1126@yahoo.com or kimphillips14@gmail.com

Saturday, October 08, 2011

5 Facts About Pancreatic Cancer


Shape Magazine Online
Thursday, 10/6/2011 at 12:01:29 PM

1. Pancreatic cancer is one of the few cancers for which survival has not improved substantially over nearly 40 years. According to the American Cancer Society (ACS), not many advances have been made when it comes to pancreatic cancer. In fact, pancreatic cancer is the fourth leading cause of cancer-related death in the United States. An estimated 44,030 Americans will be diagnosed with pancreatic cancer in the U.S., and more than 37,660 will die from the disease.


2. Pancreatic cancer has the highest mortality rate of all major cancers. It's estimated by the ACS that 94 percent of pancreatic cancer patients will die within five years of diagnosis, and only 6 percent will survive more than five years. A total of 74 percent of patients die within the first year of a pancreatic cancer diagnosis.


3. Genetics plays a role. Like most diseases and cancers, a family history of pancreatic cancer is a risk factor.


4. Smoking, obesity and heavy drinking has been linked to pancreatic cancer. Lifestyle choices can affect your risk of getting pancreatic cancer. According to WebMD, the unhealthy practices of smoking, weighing too much and drinking heavily, all can increase your risk.


5. Pancreatic cancer can be hard to diagnosis early. Because pancreatic cancer may only cause vague symptoms — such as abdominal or back pain, weight loss, jaundice, loss of appetite, nausea, changes in stool and diabetes — many times pancreatic cancer is misdiagnosed as GI issues until the cancer has progressed.


Jennipher Walters is the CEO and co-founder of the healthy living websites FitBottomedGirls.com and FitBottomedMamas.com. A certified personal trainer, lifestyle and weight management coach and group exercise instructor, she also holds an MA in health journalism and regularly writes about all things fitness and wellness for various online publications.

Tailored breast cancer drugs in focus at cancer meet


ZURICH | Tue Sep 20, 2011 11:50am EDT


ZURICH (Reuters) - Doctors and investors at a cancer conference starting on Friday will be keen to find out more on the effectiveness of two promising new breast cancer drugs from Swiss drugmakers Roche and Novartis.

Roche's T-DM1 and Novartis's Afinitor have been designed to treat two specific types of breast cancer and are among the latest examples of the tailored therapies increasingly being used in oncology.
A mid-stage trial has already shown recently that T-DM1, which combines Roche's Herceptin with a potent cell-killing payload delivered directly to cancer cells, helped patients live longer without their disease getting worse compared with those taking Herceptin and conventional chemotherapy.
It also showed that T-DM1 had fewer side effects. Investors will eye the more detailed data sets to see the size of the benefit and whether the reduced side effects increased patients' likelihood of sticking with the treatment.

Roche and Novartis, the top two global players in oncology, are due to present more detailed data on their drugs at the EMCC European cancer congress, which runs from September 23-27 in Stockholm.
"We have further data at the next cancer conference, and we believe they are quite astounding," Stefan Frings, Global Head of Medical Affairs Oncology at Roche, told Reuters at the group's headquarters in Basel.

Roche hopes the T-DM1 results will help it protect its multibillion-dollar Herceptin franchise even as Herceptin loses exclusivity in the coming years.

T-DM1, which Roche is developing with Immunogen, is a new kind of "armed antibody."

The fact that the drug delivers its toxic payload directly into cells is thought to be key to why it causes fewer cases of common chemotherapy side effects such as hair loss and low white blood cell counts.

"For T-DM1 we want to know more about the extent of those benefits as that ultimately has an impact on the pricing issue, which is important for Roche as they seek to combine more products to treat breast cancer," Helvea analyst Karl-Heinz Koch said.

Novartis has also sounded an upbeat note about the prospects for Afinitor, also known as everolimus, which is already approved for other types of cancer, such as kidney and a rare type of pancreatic cancer.
CEO Joe Jimenez told Reuters in a recent interview it could generate sales of at least $1 billion if it makes it to the market for patients with hormone-sensitive breast cancer. It is planning to file for regulatory approval by the end of 2012.

The interim analysis of a late-stage trial showed Afinitor taken with Pfizer's oestrogen-blocker Aromasin, also known as exemestane, extended the time patients lived without their tumor growing.
More details from the BOLERO-2 study will be presented in Stockholm.

Novartis is seeking to use Afinitor, which works by targeting the protein mTOR in cancer cells, to treat women with hormonal receptor-positive breast cancer who have not responded to initial hormonal therapy.
"After around 25 years of hormonal therapy for this type of patient population, this study represents a really innovative therapy that is a step forward for this group of patients with breast cancer," Alessandro Riva, Global Head of Oncology Development and Medical Affairs at Novartis, told Reuters.

Worldwide, there are approximately 220,000 newly diagnosed cases of ER+HER2- advanced breast cancer each year that could benefit from Afinitor, Riva said, adding the drug was well tolerated and can be taken over a prolonged period.

"The breast cancer story is a very nice journey for everolimus," Riva said. "The journey is not finished because we have a large program now ongoing in the HER2-positive metastatic breast cancer patients."

TAKING AIM
Targeted therapies are treatments that use drugs to identify and attack specific cancer cells without harming normal cells. Monoclonal antibodies, such as Herceptin, and tyrosine kinase inhibitors, such as GlaxoSmithKline's Tykerb, are two types of targeted therapies used in breast cancer.
Roche first broke ground in this field just over a decade ago with Herceptin, which was designed to treat women with breast cancer who make too much of the HER2 protein. About 20 percent of breast cancer patients have these particularly aggressive types of tumors.

It is now also developing pertuzumab, another medication for women with HER2-positive metastatic breast cancer, which it is ultimately hoping to use with T-DM1 to attack the cancer on several different fronts.
Roche is planning to file for approval of pertuzumab this year after positive results from a late-stage trial.
Roche's and Novartis's bid to combine treatments comes as scientists increasingly understand that cancer cells are able to keep growing by finding ways to outmaneuver treatments, so using a cocktail of drugs could be key to the fight.

AFINITOR VS AVASTIN
Afinitor may also be able to capitalize on the recent woes of another of Roche's cancer drugs, Avastin, which was once tipped to become the world's best-selling drug.

U.S. authorities proposed revoking its approval in advanced breast cancer at the end of last year, a decision that dented sales of Avastin in breast cancer on both sides of the Atlantic.

A few months later, advisers to the Food and Drug Administration agreed that the drug was not safe or clinically beneficial, dealing a blow to Roche and also to those patients who had insisted it had saved their lives.

"Afinitor could bring in at least $1.5 billion in sales in the second line HER2-advanced breast cancer setting, and if Novartis could extend use to the first line as well, sales could increase to around $4 or $5 billion," Helvea's Koch said.

"The only competition out there at the moment is Avastin, but it has been knocked off its throne in the United States and also to a large extent in Europe," Koch said.
(Editing by Kate Kelland and Will Waterman)

Friday, October 07, 2011

Pancreatic cancer declining, but among most deadly

(10-06) 18:49 PDT (AP) --
Pancreatic cancer is notoriously lethal — there are almost as many deaths from it each year as there are new cases. The deaths this week of Apple founder Steve Jobs and Nobelist Ralph Steinman bring unusual attention to this less-well-known type of cancer that has actually been declining despite no big advances in treatment or finding it early.


A decline in smoking, one of the top risk factors for the disease, may be behind the drop in cases.


Jobs lived more than seven years after being diagnosed with a neuroendocrine tumor — a less common, slower-growing and more treatable type of pancreatic cancer than the kind that killed Steinman a week ago and actor Patrick Swayze two years ago.
The Apple chief kept details of his illness behind a firewall and declared he was cured after cancer surgery in 2004. However, five years later, gaunt and having lost a lot of weight, Jobs had a liver transplant. Experts said it was likely because his cancer had returned or spread.


A liver transplant sometimes can cure the type of cancer that Jobs had. But if it comes back, "it's usually in one to two years," said Dr. Michael Pishvaian of Georgetown University's Lombardi Comprehensive Cancer Center.


In January, Jobs announced his third and final leave of absence. He resigned in August and died on Wednesday.


Part of what makes pancreatic cancer so deadly is that the pancreas is as vital as the heart. You can live with just part of a liver or a colon, or only one kidney or lung. But the pancreas is a fish-shaped organ that makes digestive enzymes and insulin and other hormones that enable the body to make energy from food.


In the United States, pancreatic cancer is the fourth leading cause of cancer deaths. About 44,030 people will be diagnosed with it and about 37,660 people will die of it this year in the U.S., the American Cancer Society estimates.


Possible symptoms are fatigue, back pain, abdominal pain, unexplained weight loss, loss of appetite, jaundice and nausea, according to the Lustgarten Foundation, a private group that finances research on the disease.


This cancer often is not found until it is advanced or has spread, and overall survival is dismal: 20 percent after one year and only 4 percent after five years.


However, with a neuroendocrine tumor like the one Jobs had, "people can live a longer time; median survival is five to eight years," said Dr. Alan Venook, a pancreatic cancer specialist at the University of California, San Francisco.


The lifetime risk of developing pancreatic cancer is about 1 in 71, according to the cancer society. Men and blacks account for more cases than women and whites, possibly because of differences in smoking rates. Smokers have two to three times more risk of developing the disease. Use of smokeless tobacco also raises the risk.
Obese people, those who don't exercise much and diabetics also have more risk for pancreatic cancer. Alcohol use might play a role: Most studies haven't tied it to pancreatic cancer, but heavy drinking can lead to diabetes and liver and pancreas problems that pose a cancer risk, the cancer society says.


The best hope for a patient is that the tumor is operable. That was the case in February 2009, when U.S. Supreme Court Justice Ruth Bader Ginsburg had a small, early-stage pancreatic tumor removed at New York's Memorial Sloan-Kettering Cancer Center.
On the horizon are immune system treatments — research that Steinman, the Nobel recipient from Rockefeller University in New York, was studying in the lab and trying on his own pancreatic cancer.


The immune system has a hard time recognizing and fighting cancer because the enemy is not an invading germ but our own cells gone rogue. Treatments called therapeutic cancer vaccines are ways to modify cells to help the immune system recognize the risk.


One such vaccine by NewLink Genetics, a small biotech firm in Ames, Iowa, is in late-stage testing now for pancreatic cancer. The company website says the larger study was initiated after a mid-stage test suggested improvement in survival.


Dr. Roderich Schwarz, chief of surgical oncology at the University of Texas Southwestern Medical Center in Dallas, has enrolled a few patients in some immune therapy studies, which have not paid off in the past.


"Vaccines are coming along," and last year's approval of one for advanced prostate cancer suggests researchers may be learning to overcome some of the drawbacks of the past, he said.


"It's quite possible that vaccines will claim their territory in the treatment of these challenging tumors," Schwarz said. "It's still in the development stage rather than the proven stage."
___
Online:
Cancer Institute: www.cancer.gov/cancertopics/types/pancreatic
Cancer Society: www.cancer.org/Cancer/PancreaticCancer/index
Survival rates: http://bit.ly/oAxKl5
Research and support: www.curePC.org and www.lustgarten.org
Vaccine study: www.linkp.com/products/hyperacute-pancreas.html

Blood clots more common than thought: Study

First posted: | Updated:
Research from Duke University has found blood clots are more common in cancer patients than doctors may realize.

An analysis of more than 30,000 cancer patients found as many as one in five patients are at risk of developing a blood clot within a year of getting treatment.

In up to 2% of cases, the clots are deadly.

The risk of developing a clot within four months of starting treatment varied widely depending on the type of cancer diagnosed. Bladder cancer carries the lowest risk, at 4.8%, while pancreatic cancer has the highest risk at 11.9%.

Cancer patients who develop clots require more medication and hospitalization, which can increase the cost of treatment, the researchers said.

Lead author Gary H. Lyman said scientists don't fully understand why clots form during cancer treatment, but have identified certain contributing factors, including blood clotting agents released by tumours, side-effects of chemotherapy, and pre-existing health conditions such as obesity and anemia.

The study will be reported at the European Multidisciplinary Cancer Congress in Stockholm on Sept. 26.

http://www.torontosun.com/2011/09/20/blood-clots-more-common-than-thought-study

Thursday, October 06, 2011

The Lustgarten Foundation for Pancreatic Cancer Research Expresses Condolences for the Loss of Steve Jobs

PRESS RELEASE
Oct. 6, 2011, 11:55 a.m. EDT


BETHPAGE, N.Y., Oct. 6, 2011 /PRNewswire via COMTEX/ -- The Lustgarten Foundation, America's largest private foundation dedicated solely to funding pancreatic cancer research, today offered the following statement concerning the death of Steve Jobs, co-founder of Apple, Inc:

Kerri Kaplan, Lustgarten Foundation Executive Director, said: "The Lustgarten Foundation mourns the loss of Steve Jobs. Mr. Jobs personified bravery and vision in both his professional and personal life. While his long, courageous battle with a rare form of pancreatic cancer serves as an inspiration to all people, it also serves as a reminder that more research is urgently needed in order to find a cure. Mr. Jobs taught us that each one of us can make a difference. He was a leader and a fighter and, in that spirit, the Foundation remains committed to continuing the fight against pancreatic cancer. This is a truly immense loss."

About The Lustgarten Foundation
The Lustgarten Foundation is America's largest private foundation dedicated solely to funding pancreatic cancer research. Based in Bethpage, New York, the Foundation supports research to find a cure for pancreatic cancer, facilitates dialogue within the medical and scientific community, and educates the public about the disease through awareness campaigns and fundraising events. The Foundation has provided millions of research dollars and assembled the best scientific minds with the hope that one day, a cure can be found. For more information visit www.lustgarten.org .          

Scientists Say Blocking Chemokine Receptor in Pancreatic Cancer Stromal Cells Helps Slow Cancer Growth

GEN News Highlights: Sep 20, 2011


Scientists have demonstrated that the growth of pancreatic ductal adenocarcinoma (PDAC) in mice can be suppressed by inhibiting chemokines that act to mediate interaction between the cancer cells and fibroblasts in the stroma. Their research found that invasive PDAC cells secrete much higher levels of a number of chemokines than preinvasive pancreatic intraepithelial neoplasia (PanIN) cells, and that these chemokines stimulate stromal fibroblasts to induce connective tissue growth factor (Ctgf), a profibrotic and tumor-promoting factor, which accelerates tumor growth in vivo.

In vivo studies by the team at Vanderbilt University and the University of Tokyo showed that treating a mouse model of human PDAC using an inhibitor of the interleukin 8 receptor, CXCR2, reduced Ctgf expression and angiogenesis, slowed tumor progression, and led to increased survival. Vanderbilt’s Harold L. Moses, M.D., and the University of Tokyo’s Hideaki Ijichi, M.D., and colleagues claim the findings suggest that inhibiting tumor-stromal interaction might be a promising therapeutic strategy for PDAC. They report their findings in the Journal of Clinical Investigation, in a paper titled “Inhibiting Cxcr2 disrupts tumor-stromal interactions and improves survival in a mouse model of pancreatic ductal adenocarcinoma.”
Previous studies have suggested that development of PDAC from preinvasive PanIN occurs through a multistep progression involving the accumulation of specific genetic alterations, the team notes. Indeed, at the invasive stage, mutations and deletions in KRAS, P16INK4A, P53, and SMAD4 are found in approximately 90%, 90%, 75%, and 55% of PDAC, respectively, suggesting that alteration in these signaling pathways plays a causal, or at least permissive, role that allows progression from PanIN to PDAC in vivo.
This notion has been supported by work in various mouse models, which demonstrated that inactivating a number of these genes dramatically accelerates PDAC progression through activation of Kras. The researchers led by Drs. Moses and Ijichi had previously generated a particular mouse model of human PDAC, designated Kras+Tgfbr2KO, which develops aggressive PDAC that histologically mirrors manifestations of the disease in humans. In particular, these mice demonstrate abundant stromal components in the tumor tissue that recapitulates desmoplasia, a hallmark of PDAC histology in humans that occurs as a proliferation of fibrotic and connective tissue around the invasive tumor.

Although prior studies have indicated that desmoplasia is associated with faster tumor progression and chemoresistance, little is known about tumor-stromal interactions during tumor progression. The team hypothesized that PDAC cells may produce and release certain factors into the microenvironment to which the stromal cells could in turn respond, by establishing favorable conditions for tumor growth.
They screened for secreted factors produced by the PDAC cells from Ptf1acre/+;LSL-KrasG12D/+;Tgfbr2flox/flox PDAC tissue, and from mPanIN cells from the Ptf1acre/+;LSL-KrasG12D/+pancreas tissue. The results showed that several chemokines, cytokines, and cell surface proteins were secreted from PDAC cells at much higher levels than from mPanIN cells. These included the Cxc chemokines Cxcl1, Cxcl2, Cxcl5, and Cxcl16. Further analysis showed that expression of the chemokines was upregulated in PDAC cells at the transcriptional level.

The increased expression and secretion of cytokines prompted the investigators to look at whether the interactions between chemokines and their receptors (Cxcl1, Cxcl2, and Cxcl5 bind to Cxcr2, while Cxcl16 binds to Cxcr6) might play a role in regulating PDAC progression. They found that although the receptor Cxcr2 was detected in both normal and mPanIN pancreas epithelia, its expression was relatively prominent at the invasive front of PDAC tissue, in both the stroma and epithelium. Inhibiting expression of Cxcr2 in PDAC cells using the Cxcr2 inhibitor SB225002 had no effect on PDAC cell proliferation, which led to the notion that the increased secretion of Cxc chemokines by PDAC cells might instead be acting on the stromal cells.
Previous work has suggested that the profibrotic Ctgf may have tumor-promoting activities, and the researchers' own prior studies had also found strong expression of Ctfg at the tumor-stromal border of Ptf1acre/+;LSL-KrasG12D/+;Tgfbr2flox/flox PDAC tissues. “This suggested that an active Ctgf-dependent tumor-stromal interaction was present in the PDAC tissue that could be a therapeutic target, since the interaction increased in intensity during tumor progression,” they note.

The researchers therefore looked to see whether secretion of Cxc chemokines by PDAC cells was inducing Ctgf expression in stromal fibroblasts. QRT-PCR confirmed that the fibroblasts demonstrated much higher basal expression of Ctgf mRNA compared with the PDAC cells, and that Ctgf expression was significantly upregulated when the cells were stimulated with Cxcl1, Cxcl2, and Cxcl5. When fibroblasts were incubated with culture media taken from either PDAC cells or mPanIN cells (a control media without cells was used as a comparison), PDAC cell culture medium induced significantly higher expression level of Ctgf mRNA than mPanIN medium. Furthermore, administering either of the Cxcr2 inhibitors repertaxin or SB225002 inhibited PDAC culture medium-induced Ctgf upregulation by fibroblasts in a dose-dependent manner.

TGF-β signaling is also well known to induce Ctgf expression, and the researchers provided confirmation of this separately, by demonstrating that the Tgfbr1 inhibitor SB431542 dramatically suppressed Ctgf induction. “Taken together, the data suggest that Cxc chemokines produced by PDAC cells can stimulate pancreatic fibroblasts to express Ctgf in a Cxcr2 signal-and TGF-β signal-dependent manner,” the authors write.
To corroborate their in vitro findings in vivo, the researchers compared tumor development in nude mice injected with either PDAC cells taken from a KRAS-activated mouse tissue, or with a mixture of PDAC cells and pancreatic fibroblasts. Although animals receiving both cell types were effectively given just half the number of PDAC cells than animals receiving PDAC cells alone (all animals received the same total number of cells), the mixed-cell injection resulted in faster subcutaneous tumor growth, indicating a tumor-promoting effect of the tumor-stromal interaction. When the resulting mixed-cell tumors were treated with the Cxcr2 inhibitor repertaxin, a significant growth-inhibitory effect was observed within weeks, suggesting that the tumor-promoting effect of the observed tumor-stromal interaction was Cxcr2 dependent.
Cxcr2 was then knocked out in PDAC cells and fibroblasts, and the experiments repeated. This time animals received either Cxcr2 wild-type PDAC cells and Cxcr2-knockdown fibroblasts, or Cxcr2-knockdown PDAC cells and Cxcr2 wild-type fibroblasts. In this case it was the combination of Cxcr2 wild-type PDAC cells and Cxcr2-knockdown fibroblasts that led to slower tumor growth.

To more closely mimic a clinical situation, the researchers evaluated the antitumor effect of Cxcl-Cxcr2 axis inhibition by treating the Ptf1acre/+;LSL-KrasG12D/+;Tgfbr2flox/flox mice with repertaxin or SB225002. Another cohort of the same mouse model was treated using gemcitabine, with or without repertaxin.
While dissected tumors were generally large enough to take up most of the pancreas in control, repertaxin-treated, and SB225002-treated mice, these animals did often demonstrate areas of morphologically normal pancreatic tissue, which suggested that the inhibitor delayed the tumor development, they remark. Among gemcitabine-treated mice, tumor formation was obviously inhibited, as there was well-retained normal pancreas structure as well as focal tumor areas. Importantly, however, “morphologically normal pancreatic tissue was more frequently observed in the combination treatment with repertaxin and gemcitabine,” the authors stress.

Tumor volume measurements also showed that repertaxin or SB225002 treatment alone significantly decreased the tumor volume, and adding gemcitabine resulted in further suppression. Interestingly, the microvessel density (MVD) in the Cxcr2 inhibitor-treated tumors was significantly lower than that of the control group, while the gemcitabine-treated group did not show obvious inhibition of angiogenesis. Encouragingly, mice treated using SB225002 demonstrated statistically significant increases in overall survival.
Immunohistochemistry confirmed that Ctgf expression had been inhibited in the treatment groups, with both Cxcr2 inhibitors decreasing Ctgf expression in the remaining stroma of PDAC tissue. Gemcitabine-treated tissues, meanwhile, showed a decrease in Ctgf expression that appeared to correlate with the observed decrease of stromal volume.

“The antitumor mechanisms of gemcitabine and the Cxcr2 inhibitor were obviously different,” the authors state. “Pancreas of the mice treated with gemcitabine still retained normal structure with multiple tumor foci, while they did not show a decrease in MVD. In contrast, mice treated with Cxcr2 inhibitor showed diffuse tumor formation in the pancreas with minimal normal area remaining and significantly decreased MVD.
These apparent different mechanisms of action hinted that combining the two forms of antitumor might be a promising therapeutic strategy for PDAC. To test this, the researchers carried out a survival study in which mice were treated using either a combination of gemcitabine plus SB225002, or gemcitabine alone. The combination and gemcitabine-alone treatments showed significant survival extension compared with the control group, although unfortunately, “the combination treatment did not show an advantage in the survival data compared with the single treatment," the authors admit. Observations in some of the treated mice indicated that this may have related at least in part to dose-related drug toxicities.

Nevertheless, they conclude, “These results indicate that blockade of the Cxcl-Cxcr2 axis may be an effective adjuvant therapeutic strategy for PDAC…The combination of gemcitabine, which inhibits DNA synthesis, mainly targeting tumor cells, and Cxcr2 inhibitor, which mainly modulates tumor microenvironment and inhibits angiogenesis, might be a synergistic therapeutic strategy and may prevent excessive toxicities by allowing dose reduction of each drug.”

Wednesday, October 05, 2011

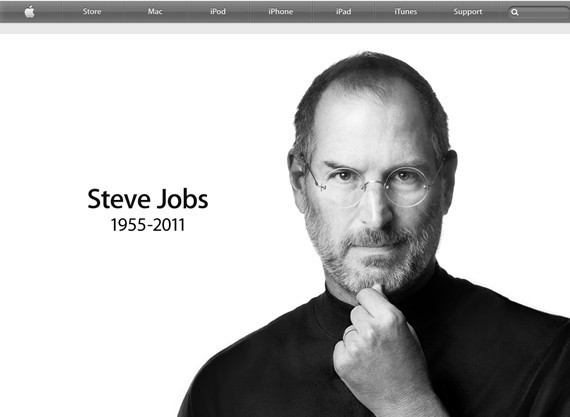
Steve Jobs Dead: Apple Co-Founder Dies At 56

More on Steve Jobs from the Huffington Post including statements from President Obama, Bill Gates and many more ...  


Apple has posted this statement on its website:
Apple has lost a visionary and creative genius, and the world has lost an amazing human being. Those of us who have been fortunate enough to know and work with Steve have lost a dear friend and an inspiring mentor. Steve leaves behind a company that only he could have built, and his spirit will forever be the foundation of Apple. 
If you would like to share your thoughts, memories, and condolences, please email rememberingsteve@apple.com
Steve Jobs' family released this statement on his passing:
Steve died peacefully today surrounded by his family.
In his public life, Steve was known as a visionary; in his private life, he cherished his family. We are thankful to the many people who have shared their wishes and prayers during the last year of Steve’s illness; a website will be provided for those who wish to offer tributes and memories.
We are grateful for the support and kindness of those who share our feelings for Steve. We know many of you will mourn with us, and we ask that you respect our privacy during our time of grief.
Apple released a statement from current CEO Tim Cook, which was sent to company employees:
Team, 
I have some very sad news to share with all of you. Steve passed away earlier today. 
Apple has lost a visionary and creative genius, and the world has lost an amazing human being. Those of us who have been fortunate enough to know and work with Steve have lost a dear friend and an inspiring mentor. Steve leaves behind a company that only he could have built, and his spirit will forever be the foundation of Apple.
We are planning a celebration of Steve's extraordinary life for Apple employees that will take place soon. If you would like to share your thoughts, memories and condolences in the interim, you can simply email rememberingsteve@apple.com.
No words can adequately express our sadness at Steve’s death or our gratitude for the opportunity to work with him. We will honor his memory by dedicating ourselves to continuing the work he loved so much.
Tim
The White House released a statement by President Barack Obama:
Michelle and I are saddened to learn of the passing of Steve Jobs. Steve was among the greatest of American innovators - brave enough to think differently, bold enough to believe he could change the world, and talented enough to do it. 
By building one of the planet’s most successful companies from his garage, he exemplified the spirit of American ingenuity. By making computers personal and putting the internet in our pockets, he made the information revolution not only accessible, but intuitive and fun. And by turning his talents to storytelling, he has brought joy to millions of children and grownups alike. Steve was fond of saying that he lived every day like it was his last. Because he did, he transformed our lives, redefined entire industries, and achieved one of the rarest feats in human history: he changed the way each of us sees the world. 
The world has lost a visionary. And there may be no greater tribute to Steve’s success than the fact that much of the world learned of his passing on a device he invented. Michelle and I send our thoughts and prayers to Steve’s wife Laurene, his family, and all those who loved him.
Obama's campaign added its condolences, tweeting from his official account: "Rest in peace, Steve Jobs. From all of us at #Obama2012, thank you for the work you make possible every day—including ours."


Bill Gates conveyed his sadness, telling AllThingsD: "I will miss Steve immensely."


Facebook's Mark Zuckerberg delivered his thanks on his official Facebook page, writing: "Steve, thank you for being a mentor and a friend. Thanks for showing that what you build can change the world. I will miss you."


Back in 2005, Jobs revealed some of his thoughts on death in a heartfelt commencement address at Stanford University, telling students: "Remembering that you are going to die is the best way I know to avoid the trap of thinking you have something to lose."


Apple.com has transformed its homepage to a tribute for its former leader.


http://www.huffingtonpost.com/2011/10/05/steve-jobs-dead_n_997223.html?icid=maing-grid7|aim|dl1|sec1_lnk3|101908

Steve Jobs Dies at 56 After Long Battle With Pancreatic Cancer


After a very long, public battle with pancreatic cancer, Steve Jobs, co-founder of Apple Inc. died Wednesday. He was 56.

"We are deeply saddened to announce that Steve Jobs passed away today," the company said in a brief statement.
"Steve's brilliance, passion and energy were the source of countless innovations that enrich and improve all of our lives. The world is immeasurably better because of Steve."

Jobs had battled cancer in 2004 and underwent a liver transplant in 2009 after taking a leave of absence for unspecified health problems.

He reportedly avoided cancer treatment early on in favor of altering his diet, but eventually had the tumor – which he said was a rare form called an islet cell neuroendocrine tumor – successfully removed.

About 85 to 90 percent of people who have liver transplants will be alive one year later, and about 75 to 85 percent of people will survive at least five years after a transplant, the United Network for Organ Sharing (UNOS) said on its website.

Patients who receive liver transplants must take immunosuppressant drugs for the rest of their lives to limit their risk for rejection.

But while these drugs serve their purpose, a compromised immune system can leave patients vulnerable to other diseases.

Jobs took another leave of absence in January -- his third since his health problems began -- before resigning as CEO six weeks ago. Jobs became Apple's chairman and handed the CEO job over to his hand-picked successor, Tim Cook.

Most pancreatic cancer cases are asymptomatic, meaning patients rarely exhibit symptoms of an illness until it's too late to stop its spread.

Caught in its advanced stages, pancreatic cancer, which affects about 30,000 people a year, has a 5 percent survival rate for five years. Caught early enough and treated with surgery and chemotherapy, the five-year survival rate goes up 17 to 25 percent.

Islet cell neuroendocrine tumors are typically a less aggressive, less common form of pancreatic cancer, representing only 1.3 percent of cases. Pancreatic cancer usually proves fatal within 4 to 6 months of diagnosis, but neuroendrocrine tumors tend to have a much better survival rate.

In 2010, there were 43,140 new cases and 36,800 deaths, according to the National Cancer Institute website. Most cases aren’t diagnosed until it reaches the later stages, making it the fourth leading cause of death in both men and women. Patients are typically in their mid-to-late 60s and cases are usually sporadic.

But there are risk factors including smoking, heavy drinking, and in some cases a genetic predisposition for the disease. Some sufferers of chronic pancreatitis may also be at risk.

Besides eating right and abstaining from smoking and heavy drinking, there's very little that can be done to prevent the disease.

In 2005, following the bout with cancer, Jobs delivered Stanford University's commencement speech:
"Remembering that I'll be dead soon is the most important tool I've ever encountered to help me make the big choices in life," he said. "Because almost everything -- all external expectations, all pride, all fear of embarrassment or failure -- these things just fall away in the face of death, leaving only what is truly important."

The Associated Press and FoxNews.com's Karlie Pouliot contributed to this report.

New York Yankees All-Star Pitcher David Robertson Commits to Strike Out Pancreatic Cancer

MANHATTAN BEACH, Calif., Sept. 20, 2011 /PRNewswire


David Robertson has teamed up with the Pancreatic Cancer Action Network to strike out the fourth leading cause of cancer death in the United States. As one of the organization's cause champions, Robertson will serve as Honorary Captain of TEAMHOPE®, the organization's national marathon team, at the 2011 ING New York City Marathon. In partnership with the New York Yankees, Robertson is featured in a new public service announcement to educate fans and the general public about the severity of pancreatic cancer.

Pancreatic cancer has one of the poorest relative survival rates of any cancer - 74 percent die within one year of diagnosis and the five year survival rate is just six percent. No early detection method is available and few effective treatment options exist for patients. Despite these sobering statistics, approximately two percent of the National Cancer Institute's federal research funding is allocated to pancreatic cancer. As a result, the pancreatic cancer survival rate has remained largely unchanged in over forty years.

"After learning of the staggering statistics for pancreatic cancer, I knew I needed to step up and help bring attention to this disease," stated David Robertson.  "My wife Erin and I are that much more motivated to partner with the Pancreatic Cancer Action Network having recently met local survivors and volunteers for the organization. Each of their powerful stories compelled us to take action with the Pancreatic Cancer Action Network to help beat this devastating disease."

"We applaud David and Erin for recognizing that they can make a difference by joining our efforts to advance research, support patients and create hope for the pancreatic cancer community," said Julie Fleshman, President and CEO of the Pancreatic Cancer Action Network. "They will be wonderful partners for the Pancreatic Cancer Action Network as we work diligently to double the survival rate for pancreatic cancer by 2020.  Having supporters like the Robertsons, who have no personal connection to the disease but fully understand how insidious and difficult pancreatic cancer is, helps us build greater awareness and attract other advocates from the general public to our cause."

This year, it is estimated 44,030 people in the United States will be diagnosed with pancreatic cancer and 37,660 will die from the disease. "I know, as a team, we can make a difference and bring greater hope to loved ones and friends who will face this leading cancer killer," added Robertson.
To learn more about the Pancreatic Cancer Action Network, visit www.pancan.org. For more information on TEAMHOPE® and how you can join future marathon teams, go to www.iamteamhope.org.

About the Pancreatic Cancer Action Network
The Pancreatic Cancer Action Network is the national organization creating hope in a comprehensive way through research, patient support, community outreach and advocacy for a cure. The organization is leading the way to increase the survival rate for people diagnosed with this devastating disease through a bold initiative—The Vision of Progress: Double the Pancreatic Cancer Survival Rate by 2020. Together, we can know, fight and end pancreatic cancer by intensifying our efforts to heighten awareness, raise funds for comprehensive private research, and advocate for dedicated federal research to advance early diagnostics, better treatments and increase chances of survival.

Available Topic Expert(s): For information on the listed expert(s), click appropriate link.
Julie Fleshman
http://www.profnetconnect.com/julie_fleshman


SOURCE Pancreatic Cancer Action Network
Back to top RELATED LINKS
http://www.pancan.org

Tuesday, October 04, 2011

From a Colorado colleague: Soda increases Pancreatic Cancer Risk

Pancreatic cancer and soda consumption:
Jacob Schor ND FABNO
February 13, 2010

An odd coincidence in timing:
Perhaps it is because soda and candy have been a big story in Colorado legislative news over the last few months, that an article in an obscure epidemiology journal caught my attention this past week.  Back in November 2009 Colorado’s currently democratic leadership announced plans to add a 2.9% tax to carbonated beverages and candy as part of a comprehensive plan to balance the state budget.  The bill to turn Governor Ritter’s soda tax proposal into law was passed by the Colorado Senate just a few days ago. The lead up debate to this vote brought forth vocal opponents that made it apparent that many people believe unfettered access to soft drinks is a fundamental right guaranteed in the Constitution.

Coincident with these Colorado legislative debates, but unmentioned, is a fascinating paper by Noel Mueller et al. that appeared in the February issue of Cancer Epidemiology, Biomarkers & Prevention.  According to their analysis, drinking two or more sodas a week almost doubles a person’s risk of getting pancreatic cancer.

Their data was collected from a prospective cohort made up of 60,524 people who are taking part in the Singapore Chinese Health Study. Information on consumption of soft drinks, juice, and other dietary items, as well as lifestyle and environmental exposures, was collected through in-person interviews at recruitment.
Following these people for 14 years yielded 648,387 person-years of data and 140 cases of pancreatic cancer (PC). Individuals who consumed two or more soft drinks a week experienced a statistically significant increase in risk of pancreatic cancer (hazard ratio, 1.87; 95% confidence interval, 1.10-3.15) compared with individuals who did not consume soft drinks. There was no association seen between drinking fruit juice and risk of PC.

A hazard ratio of 2.0 would mean soda drinkers were twice as likely to get pancreatic cancer.  This ratio of 1.87 is just a little less than 2.0.

Background is essential to understand the results of this study.   This is just the latest in a series of studies on the subject that have yielded sometimes conflicting and confusing results.  Yet the bottom line consensus appears to be that soda or other concentrated forms of sugar, such as candy bars, do increase risk of pancreatic cancer.

The first thing we have to understand with PC is that it’s one of the bad cancers; five-year survival even with modern treatment is less than 5%.  Treatment does little good; a better approach is to focus on prevention.  Cigarette smoking is the one accepted risk factor consistently associated with increased risk of pancreatic cancer.  Type 2 diabetes also increases risk.  This led to a theory that producing high levels of insulin might somehow lead to malignant transformation of pancreatic cells.

In most cancers, the cells that become cancerous have been somehow overworked, irritated, or in some way abused prior to becoming cancer cells.  They have been pushed by something to grow faster, work harder, secrete more or in some manner live harder lives.  Estrogen pushes both breast and uterine cells to become cancerous. Testosterone pushes prostate cells to become prostate cancer. Infections push lymph cells to become lymphoma. Chronic inflammation pushes colon cancer cells, etc.  This theory about pancreatic cancer suggests that high sugar intake pushes the pancreas.   Granted, this is a vast oversimplification of both a complex process and a complicated hypothesis, but it works for my simple mind.

Diabetes has been associated with pancreatic cancer for decades. A study on Seventh Day Adventists published in 1988 reported that, “A prior history of diabetes was associated with increased risk of subsequent fatal pancreas cancer….”    Overwork cells or abuse them and they aren’t happy.
A Kaiser Permanente study published that same year, found that while cigarette smoking increased risk of pancreatic cancer by a factor of 2.5, people who had been treated for diabetes had 4.5 times the risk. (Smoking: relative risk, 2.5; 95% confidence interval, 1.3-4.7.  Diabetes: relative risk, 4.5; 95% confidence interval, 1.2-16.7).)

A Dutch paper published two years later in 1990, that analyzed data on 164 patients with pancreatic cancer, found, “…a significant, positive association between pancreatic cancer and past habitual intake of simple sugars…. (OR 1.95; 95% confidence interval 1.24-3.07).”  This led the study authors to, “… suggest that the development of exocrine pancreatic carcinoma is positively related to past habitual intake of total energy, total carbohydrates and simple sugars, …”   

A 1991 Australian paper that analyzed the habits of 104 people who developed PC also found a link to sugar consumption. “For the top quartile of refined sugar intake, the estimated relative risk was 2.21 (95% confidence interval 1.07-4.55).”

[Of course sugars aren’t the only dietary culprit in the pancreatic cancer story.  High fat diets have also been identified as a factor. A November 1993 study reported that high fat foods tripled risk.    ]
A December 1995 study that looked at 179 cases of PC in French speaking Canadians found a similar effect of sugar consumption. Again, high sugar consumption nearly tripled risk. Of interest in this paper was the pronounced effect of cooking with firewood, a habit that increased relative risk by a factor of almost 5, while cooking in a pressure cooker lowered risk to 1/3 the average.   

Sweetened carbonated drinks, what we call soft drinks, or soda, are a major source of simple sugars in western diets and as such, soda consumption provides a measure of overall sugar consumption. [16]   Soda consumption is associated with hyperglycemia and hyperinsulinemia, obesity and type 2 diabetes.   

Let us return to the current study by Mueller and colleagues.  Rates of developing pancreatic cancer have plateaued and are stable in the United States but they are rising among Chinese men and women in Singapore. From 1968 to 1998 they have almost doubled going from 3.7 to 5.4 per 100,000 for men and 1.5 to 3.4 per 100,000 for women. One explanation for this increase is the shift toward a more western diet and increased consumption of sugar and sugar sweetened sodas.  It may be that during this transition period between traditional diets and western diets that the effect of soda consumption is more pronounced.  Soda may be adopted into the diet while traditional foods and recipes still comprise the basic diet.

On the other hand as soda consumption increases so do other behaviors linked to higher risk of pancreatic cancer.  For example in the Mueller study, people who drank more soda also consumed more red meat, total fat, sugar, candy, and alcohol.  They smoked more, exercised less and were more likely to become diabetic.  Is soda the cause of the increased risk or is it just a marker of overall poor lifestyle?  The intricate dissection of this data using statistical tools is a delicate task.  Simply gathering data on so rare a cancer is itself a challenge.

In the last five years four other prospective cohort studies have been published that looked at this same equation of soda or sugar consumption and whether it is tied to pancreatic cancer risk. (Schernhammer, Larsson, Nothlings, Bao)  Results from the current Mueller paper are consistent with three out of four of these earlier studies.  One other study included fruit juice and found a positive association between juice intake and PC risk; this current study did not find an association.

Eva Schernhammer and researchers from Harvard used data from two large cohorts, the Nurses' Health Study and the Health Professionals Follow-up Study, comprising 88,794 women and 49,364 men for their 2005 paper. These cohorts over the course of 20 years follow-up yielded data on 379 cases of pancreatic cancer.  Schernhammer’s analysis found that the women who consumed more than 3 sodas a week had a 57% greater risk of pancreatic cancer than women who drank one or less sodas a month. (RR, 1.57; 95% CI, 1.02-2.41; P for trend = 0.05). No association was found in the 174 men who developed pancreatic cancer.

In November 2006, the American Journal of Clinical nutrition published a paper by Susanna Larsson et al, analyzing Swedish dietary data from a cohort of 77,797 people who were followed for 7 years, 131 of whom developed pancreatic cancer. Those who drank 2 or more soft drinks a day had a 93% increased risk of pancreatic cancer. (OR1.93 (1.18, 3.14; P for trend = 0.02)   

A November 2007 study conducted by Nothlings and fellow researchers from the University of Hawaii analyzed data for 162,150 participants in the Hawaii-Los Angeles Multiethnic Cohort Study to investigate associations between glycemic load, dietary carbohydrates, sucrose, fructose, total sugars, and added sugars and the risk of pancreatic cancer.  During 8 years of follow-up, 434 pancreatic cancer cases occurred within the group.  Again the results though suggestive contradict, at least in part, other studies. The risk of PC increased with higher intakes of total sugars, fructose, and sucrose. The association with fructose was significant when the highest and lowest quartiles were compared (relative risk: 1.35; 95% CI: 1.02, 1.80; P for trend = 0.046). An almost identical association was found with high fruit and juice intake (1.37; 1.02, 1.84; P for trend = 0.04).  But no association was seen with soda intake.  The researchers concluded that, “High fructose and sucrose intakes may

play a role in pancreatic cancer etiology. Conditions such as overweight or obesity in which a degree of insulin resistance may be present may also be important.”

The Bao study published in 2008 is the one report that did not find an association between sugar and PC.  This is despite the fact that it was the largest of the studies.  Rather than soda they calculated the total consumption of added sugar and sugar-sweetened foods and beverages, examining data from 487,922 men and women calculating total added dietary sugar intake. During 7.2 years of follow-up, 1,258 pancreatic cancer cases were found within the group. The lowest sugar consumers averaged about 3 tsp/day while the high consumers averaged almost 23 tsp/day.  No difference in risk was seen between these two groups.  We should clarify; no statistically significant difference was seen.  The low sugar consumers had a relative risk of 0.85 compared to the high sugar eaters but this did not reach statistical significance. Thus these results did not support the sugar hypothesis.   

Just a year later in August 2009, another study reported different results, a positive but still confusing, association.  June Chan and colleagues from the University of California in San Francisco reported in the journal Cancer Causes and Control on a comparison of the dietary habits of 532 people who developed PC with people who didn’t. “Among men, greater intakes of total and specific sweets were associated with pancreatic cancer risk…” that ranged from an overall risk of 1.9 for total sweets to 3.3 for candy bars but in this study,  “…Sweets were not consistently associated with risk among women.” In contrast to other soda studies they also reported that,  “Sweetened beverages were not associated with increased pancreatic cancer risk.”  But to confuse things further,  “… low-calorie soft drinks were associated with increased risk among men…”  

In November 2009 an Italian study was published that once again supported a link between sugar consumption and pancreatic cancer.  Polesel et al. worked with data from 326 patients with pancreatic cancer comparing them to 652 control patients. Comparing the diets of the two groups they found that, “Frequent meat consumption was associated to a twofold increased risk of pancreatic cancer (95% CI: 1.18-3.36). Added table sugar (OR = 2.23; 95% CI: 1.34-3.71) and potatoes (OR = 1.79; 95% CI: 1.12-2.86) were related to pancreatic cancer.”  Leading them to conclude that, “The increased risk for table sugar suggests that insulin resistance may play a role in pancreatic carcinogenesis.”
Thus the results of the Mueller study do not stand-alone but are one of a series of studies that have parsed out this relationship between sugar and pancreatic cancer.  If we are to accept these findings though we need an explanation to explain this relationship.

There are two types of pancreatic cancer, endocrine or exocrine; endocrine tumors develop in the hormone producing tissues for secretion into the blood while exocrine cancers develop from the tissues that make digestive enzymes for secretion into the intestine.  “Of pancreatic tumors, 95% develop from the exocrine portion of the pancreas, including the ductal epithelium, acinar cells, connective tissue, and lymphatic tissue.”    These exocrine derived are the focus of this discussion.

“It is tacitly assumed that the endocrine and exocrine parts of the pancreas are independent of each other, almost as though they were anatomically related by some sort of celestial coincidence.”  But this is not the case.  Instead, “…the two components are functionally related, and that the endocrine gland exerts a profound effect upon the digestive activities of the organ.”  Blood and with it, insulin, are carried from insulin producing cells to exocrine cells in what has been named the Insulin-Pancreatic Acinar Axis.  Insulin regulates the exocrine function of the pancreas. Exocrine cells are exposed to insulin concentrations that are 20-fold higher than in general circulation. Insulin has an effect on these cells increasing cell division and stimulating production of amylase.      These high insulin levels may increase free insulin-like growth factor (IGF) by lowering levels of IGF-binding proteins.  Low levels of IGF-binding proteins are suggested in some research to be risk factor for pancreatic cancer.   

[It should be noted that not all studies support this idea; an August 2009 paper found no link between IGF-1 or IGF-binding proteins and PC.  ]

The Mueller paper found no association between fasting plasma insulin levels and pancreatic cancer risk. “This suggests that postprandial insulin may be a better measure for the association with cancer risk than fasting insulin levels and is consistent with the independent role of soft drink consumption in the development of pancreatic cancer….”   In other words it may be the surge of insulin produced after eating concentrated sugars that is the problem.
Abandoning these soda studies for a moment, this idea that elevated insulin levels increase cancer risk is supported by a paper published in September 2009 in Diabetologia. Currie and colleagues at Cardiff University looked for confirmation of this insulin theory by looking at the effects of different blood sugar lowering treatments on type 2 diabetics.
They analyzed a retrospective cohort of 62,809 people who developed diabetes after age 40 and who were treated with either oral agents or insulin. These patients were divided into four groups according to whether they received monotherapy with metformin or sulfonylurea, combined therapy (metformin plus sulfonylurea), or insulin. The outcome measures were progression to any solid tumor, or cancer of the breast, colon, pancreas or prostate.  “Metformin monotherapy carried the lowest risk of cancer. In comparison, the adjusted HR was 1.08 (95% CI 0.96-1.21) for metformin plus sulfonylurea, 1.36 (95% CI 1.19-1.54) for sulfonylurea monotherapy, and 1.42 (95% CI 1.27-1.60) for insulin-based regimens. Adding metformin to insulin reduced progression to cancer (HR 0.54, 95% CI 0.43-0.66). …. Compared with metformin, insulin therapy increased the risk of colorectal (HR 1.69, 95% CI 1.23-2.33) or pancreatic cancer (HR 4.63, 95% CI 2.64-8.10),…..  Sulfonylureas were associated with a similar pattern of risk as insulin.”  It appears anything that increases insulin levels whether it is oral hypoglycemic drugs or actual insulin increased risk of some cancers, especially pancreatic cancer risk.

Back to Colorado’s ‘Soda Tax’ for a moment.  One of the arguments against taxing soda was that the price increase would dissuade consumers from purchasing it and therefore harm Colorado businesses and beverage dealers leading to job losses. Ignorant as I am about the economics of junk food marketing, I find it difficult to believe that a 2.9% price increase would influence anyone’s purchase decision to such an extent.
Given the concerns raised by these studies regarding the health impact soda has, the tax sounds far too low as it will do little to shift consumption patterns.   Perhaps my views are swayed by the task of sitting with people every day who ask me why they have cancer.  A better argument against the soda and candy tax might be that they will effectively lower consumption and eventually cut pancreatic cancer incidence by half leading to unemployment among oncologists. We should be so lucky!

http://www.gfdoctor.com/?tag=pancreaticcancer

A version of this newsletter is posted on our website with abstracts of all or almost all of the studies mentioned.

http://denvernaturopathic.com/sodaandPC.htm

Dr. Jean M. Layton
1329 King Street
Bellingham WA 98229

twitter: GFDoctor
Facebook: GFDoctor

Monday, October 03, 2011

Living a Gluten-Free Life. Can it help ward off pancreatic and other intestinal cancers?

From the Huffington Post
http://www.huffingtonpost.com/glenn-d-braunstein-md/living-a-gluten-free-life_b_602867.html


Strolling through the aisles at Whole Foods or one of the other fancy specialty grocery stores that dot Los Angeles, a label you will start seeing more and more is "gluten-free."

It's not part of a new fad diet craze - though, more and more people are adopting a gluten-free lifestyle because they find it has a number of health benefits. These products are intended to help those who have celiac disease, a lifelong digestive disorder that is affecting a growing number of people. It's estimated to affect about 1 percent of the world's population, and about 1 in 133 Americans have been diagnosed with it. However, the actual numbers may be far greater. Many medical experts suspect this is only the tip of the celiac iceberg.

When people with celiac disease, or CD, eat foods that contain gluten, it triggers their immune system to set off a toxic reaction that can damage the villi - tiny hair-like projections in the small intestine - and prevent basic nutrients from food such as protein, carbohydrates, fats, vitamins and minerals from being properly absorbed.

Gluten refers to proteins in specific grains, including all forms of wheat (durum, semolina, spelt and others) and grains such as rye, barley and triticale. Avoiding these proteins is a necessity for those with CD, and it's no easy task. Check the labels the next time you're buying groceries to see just how prevalent gluten is. Breads, crackers and pasta are all off the menu for CD sufferers.

The disease largely goes undiagnosed, in part because many physicians don't recognize its symptoms or its symptoms can be so vague that they're not recognizable. For instance, occasional bouts of diarrhea, abdominal cramping, intestinal gas, distention, occasional constipation and occasional bloating are all symptoms of celiac disease. And who hasn't experienced a few of those from time to time?
Sometimes it's discovered when a patient is anemic, and yet no cause can be found for the blood to be lacking iron, or when weight loss occurs despite a voracious appetite.

CD has been mistaken as a gastrointestinal disorder or a food allergy. It's neither. It's an autoimmune disease that affects multiple systems in the body. The disease is more than a matter of discomfort for those who have it. If undiagnosed, it can lead to a number of serious conditions including iron deficiency anemia and osteoporosis, as well as an increased risk of certain cancers including lymphoma.

The treatment for CD is strict adherence to a gluten-free diet. The upside to the diet is that it's extremely effective. Eliminating the pesky protein often makes patients feel significantly better within two weeks.
Peter Green, M.D., director of the Celiac Disease Center at Columbia University, recently shared an anecdote when he spoke to medical faculty at Cedars-Sinai Medical Center to illustrate just how sensitive patients with CD are to wheat. One patient was extremely faithful to her gluten-free diet, making only a single exception: the communion wafer she took during mass at her Catholic church. That tiny morsel was enough to keep her symptoms going despite all of her other efforts.

Don't even think about disturbing a gluten-free gourmet's culinary efforts. Just dipping a cracker into a sauce to steal a taste will be cause to have to start over from scratch.

You'd be amazed how many unexpected places gluten crops up. Starchy products like breads, pastas, crackers and cereals are obviously suspect. But labels that don't mention wheat or gluten, but contain malt (which is made from barley) or hydrolyzed vegetable protein (often containing wheat) are also suspect.
Fortunately, more products are becoming more widely available for those dodging gluten. For example, there are breads made with rice or potato flour instead of wheat. While some classic cereals, like cream of wheat, are out of the question, rice and corn cereals are good alternatives.

A nice grilled steak with vegetables, and rice or a baked potato would be a perfectly acceptable menu for your average gluten-free dinner guest. For the pre-meal dips, just swap out crackers with rice cakes. While a toast with a couple of frosty beers isn't feasible, wines are generally gluten-free.

If you think you have celiac disease, check with your doctor. The condition can be diagnosed through specific antibody tests in the blood, and confirmed with a small bowel biopsy. Blood tests can only screen for the risk of the disease or rule it out - but cannot confirm it. The cause is unknown, but genetics seem to play a large role.

For the newly-diagnosed, there are many resources available from your doctor, as well as many online communities devoted to creative celiac-friendly cuisine. A good place to start is the Celiac Disease Foundation (http://www.celiac.org), a national organization that has been raising awareness of celiac disease since 1990. Its website has lots of great information, including a diet guide on good and bad food categories for those with CD, as well as links to other online resources.
 
Follow Glenn D. Braunstein, M.D. on Twitter: www.twitter.com/CedarsSinai